

What human studies show about testosterone peptides, where safety evidence is limited, and what to discuss with a clinician.
- Hormone responses do not establish treatment benefit.
- Safety evidence varies by substance and route.
- Symptoms need assessment before treatment.
Bottom line Bring your symptoms and complete medicine list to a clinical appointment before considering a hormone intervention.

What peptides increase testosterone? Kisspeptin has increased reproductive hormone activity, including testosterone in some human studies. That does not establish an effective, safe long-term treatment for men with low testosterone. Ipamorelin, CJC-1295 and BPC-157 should not be presented as proven testosterone therapies or automatically safer substitutes for prescribed testosterone.
The Prime Perspective
The useful question is not which molecule sounds most advanced. It is whether a treatment has been shown to help people with your actual condition, at an acceptable risk. This is an editorial evidence review, not medical advice or a clinician-reviewed treatment guide. We do not recommend peptide suppliers, injections or self-directed protocols.
Our editorial policy sets out how we handle evidence. Research illustrations on this page are AI-generated conceptual images, not photographs of study participants or a medical consultation.

What the Human Research Actually Shows
Kisspeptin: a research signal with important limits
Kisspeptin acts upstream in reproductive hormone signaling. It can stimulate gonadotropin-releasing hormone pathways, which influence luteinizing hormone and testosterone production. In a human kisspeptin-10 study, researchers observed LH stimulation and increased testosterone during infusion. That establishes a measurable response under study conditions; it does not show that a product sold online treats age-related symptoms.
A small study in healthy older men also examined responsiveness. Only five older men participated, and their testosterone response was reduced relative to younger men. Such a sample cannot settle long-term effectiveness, fertility outcomes or safety for a broad population.
Newer research includes a 2026 report of sustained hormonal responses over 12 days. This adds evidence about short-duration hormone signaling in healthy men. Twelve days still does not establish months or years of symptom improvement, cardiovascular safety or effectiveness in men with diagnosed hypogonadism.
Why growth hormone claims do not answer the testosterone question
Ipamorelin and CJC-1295 are discussed in relation to growth hormone pathways. A claim about growth hormone, sleep or body composition cannot be substituted for a controlled demonstration of a clinically useful testosterone treatment. BPC-157 is also marketed for unrelated recovery claims; that does not make it an established testosterone intervention.
On a small screen, swipe the table sideways to read every column.
| Substance or claim | What can be said | What cannot be concluded |
|---|---|---|
| Kisspeptin | Human studies show reproductive hormone responses under defined conditions. | That self-treatment improves long-term health or symptoms. |
| Gonadorelin / GnRH | A reproductive hormone signal used in specific medical contexts. | That a generic intermittent protocol replaces diagnosis or preserves fertility for every TRT user. |
| Ipamorelin / CJC-1295 | Growth hormone pathway claims require their own evidence. | That they are proven low-risk testosterone boosters. |
| BPC-157 | There are major gaps in human safety information. | That recovery marketing establishes testosterone benefit or high safety. |
Three Human Kisspeptin Studies, Compared
These studies examine reproductive hormone responses. The participant counts below belong to different protocols and must not be added together as though they were one large treatment trial. In particular, healthy volunteers are not interchangeable with men who have diagnosed hypogonadism and persistent symptoms.
On a small screen, swipe the table sideways to read every column.
| Study | People and duration | Finding | Important limitation |
|---|---|---|---|
| 2011, kisspeptin-10; George and colleagues | Healthy men; key bolus result n=6, infusion experiments n=4. Infusions lasted up to 22.5 hours. | LH responses and increased testosterone during infusion. | Very small, short physiological experiments; no proof of long-term symptom benefit. |
| 2018, older men; study record | Five healthy older men, mean age about 59, compared with young men in the protocol. Three-hour infusions on study days. | Gonadotropin responsiveness was preserved; testosterone rises were reduced in older men. | The older men did not have late-onset hypogonadism. This is not a treatment trial in that condition. |
| 2026, repeated administration; study record | 15 healthy men recruited across experiments; 12 controls reported. Protocol arms used n=7, n=4 and n=7; repeated exposure extended to 12 days. | Sustained reproductive hormone responses in the repeated-administration protocol. | Arm counts are not independent totals. Short follow-up does not answer long-term clinical effectiveness or safety. |
The newest study is randomized, single-blinded and placebo-controlled, which is stronger than a testimonial. Its short duration and healthy-volunteer population still limit the clinical conclusion. The exact route, schedule and formulation are part of the experiment; they are not instructions to reproduce it at home.
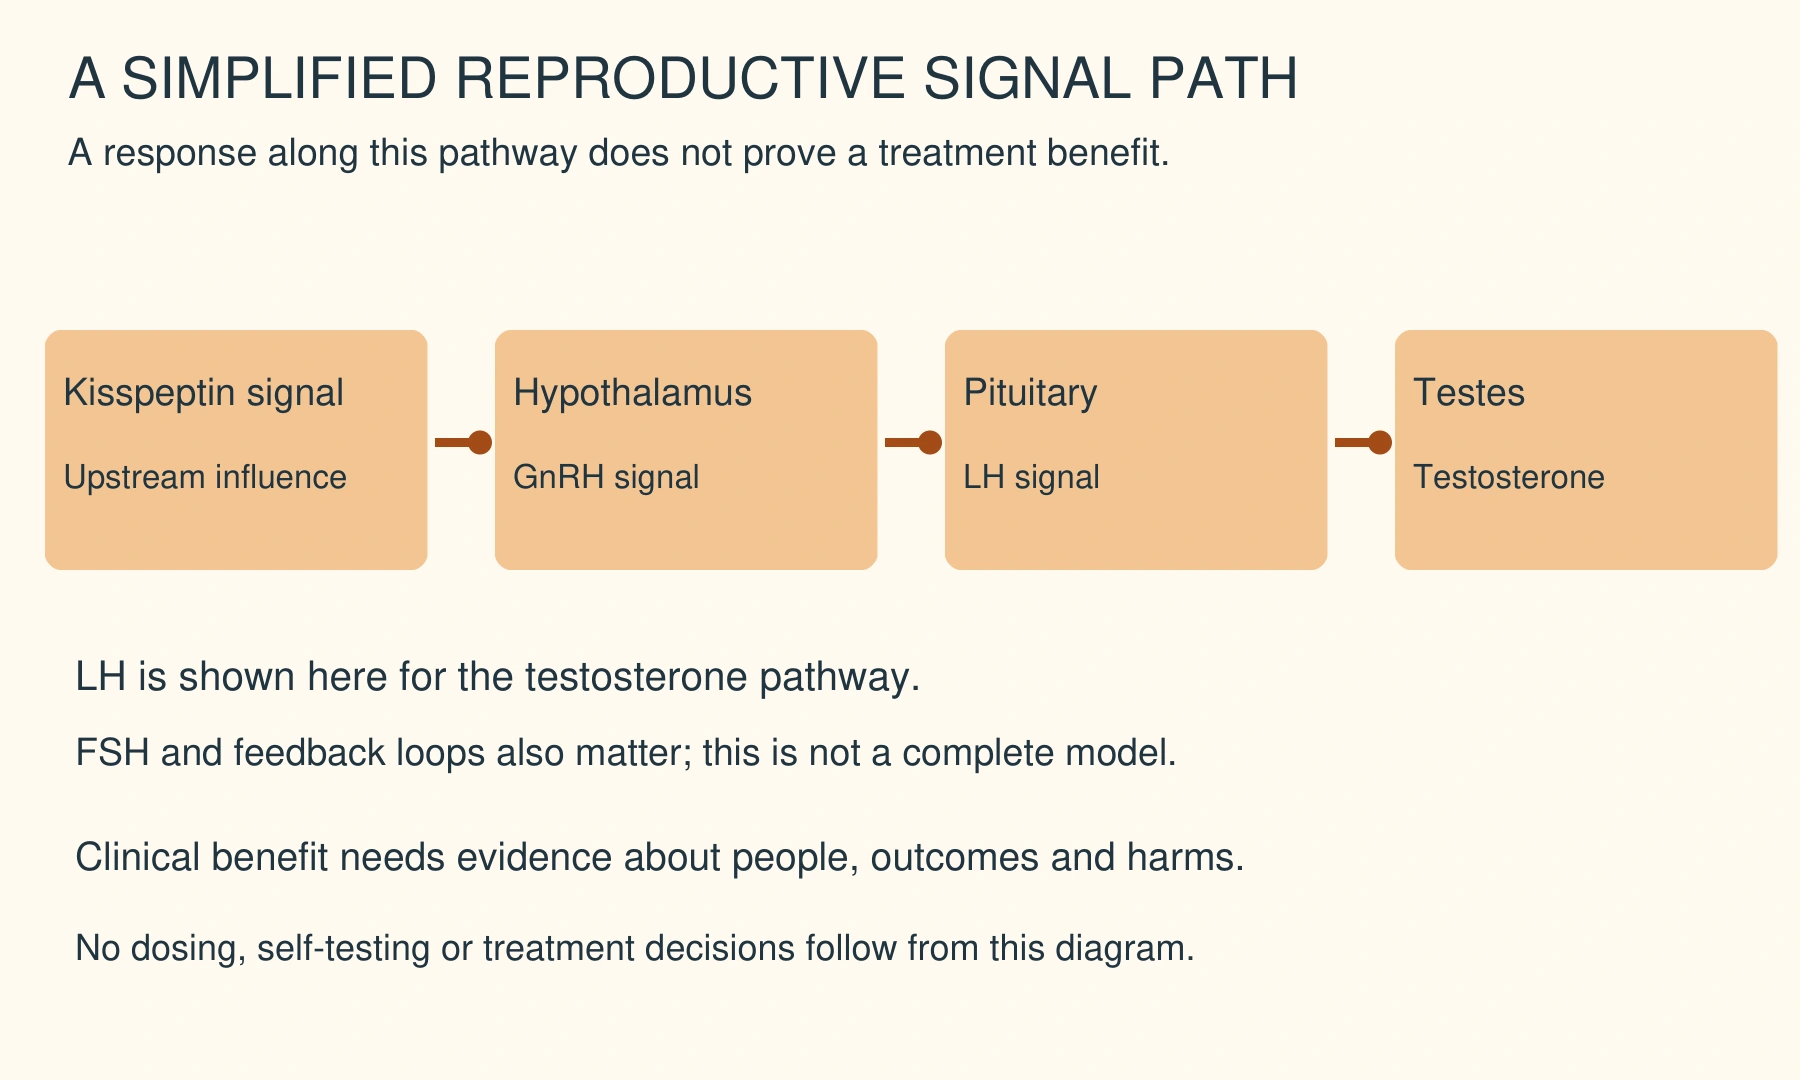
Why the Diagram Is Not a Treatment Map
A signaling pathway can respond while a person’s underlying problem remains unresolved. An upstream signal, a pituitary response and a testicular response are separate steps. The older-men study illustrates why it is misleading to assume that stronger signaling always produces the same downstream result. The diagram leaves out FSH and feedback loops for readability; it cannot locate the cause of an individual’s symptoms.
A Practical Checklist for Reading the Next Peptide Claim
On a small screen, swipe the table sideways to read every column.
| Question | Useful evidence | Reason to withhold a conclusion |
|---|---|---|
| Who was studied? | A clearly described population that matches the proposed use. | Healthy volunteers or animal findings marketed as treatment results for everyone. |
| What changed? | Patient-relevant outcomes alongside laboratory measures. | Only a hormone number, with symptom benefits assumed. |
| Compared with what? | A suitable control and a stated design. | Uncontrolled before/after stories or customer testimonials. |
| For how long? | Follow-up long enough for the benefit and harms being claimed. | Hours or days used to promise long-term safety. |
| What happened to participants? | Adverse events, withdrawals and uncertainty reported transparently. | A safety label without adequate human data. |
“Not enough evidence” does not mean researchers have proved that no future treatment could work. It means the present claim is stronger than the available evidence. Keep those two statements separate when discussing an option with a clinician. This article does not rank suppliers or offer a self-directed peptide protocol.
Download the clinician appointment questions (fillable PDF)
Save a local copy and use a PDF reader that supports form fields. Your entries are not sent to PrimeForMen.
Are Peptides Safer Than TRT?
There is no sound basis for calling this broad group automatically safer. These are different substances, with different biological effects, formulations and evidence gaps. The comparison also depends on the patient’s diagnosis and the particular prescribed treatment. “Natural signaling” is not a safety certificate.
The FDA safety assessment of compounding substances identifies limited safety information and potential immunogenicity or impurity concerns for BPC-157 and several other peptides. It reports serious adverse events associated with CJC-1295 and describes important route-specific safety uncertainties for ipamorelin. These findings do not mean every exposure produces harm; they do rule out confident blanket reassurance.
Compounding status, regulatory review and drug approval are separate questions. A pharmacy’s ability to prepare something is not proof that it has demonstrated effectiveness for low testosterone. A certificate of analysis may address a tested sample’s characteristics, but it cannot establish an effective treatment, safe personal dosing or long-term outcomes.
Start With the Cause of Symptoms
Low energy, changes in libido or reduced training performance do not identify the cause by themselves. The Endocrine Society guideline recommends diagnosing hypogonadism in men with compatible symptoms and consistently low testosterone concentrations, with repeat morning testing to confirm the result. A clinician decides what further assessment is appropriate.
That is different from ordering a universal panel because an online guide lists it. Tell the clinician about symptoms, current medicines, supplements, sleep, fertility plans and any hormones or peptides already used. Do not stop prescribed treatment based on this article.
For the broader distinction between lifestyle measures and products, see our testosterone guide for men over 40. Its general information does not replace an individual assessment.
What to Do This Week
- Write down the problem: describe what changed, when it began and how it affects daily life.
- Prepare an accurate product list: include prescription drugs and online products, with labels if available.
- Ask about evidence: which study supports the proposed use, in which patients, for how long, and with what monitoring?
- Discuss fertility before treatment: it can change the choice of therapy.
- Keep ordinary health habits proportionate: regular meals, sleep and appropriate activity support health; they are not a guaranteed correction for a hormonal disorder.
If you want a manageable activity starting point, our fitness guide for men over 50 and beginner home workouts focus on training habits. For food-first context, use the nutrition and supplements guide rather than treating another supplement as a substitute for diagnosis.
Conclusion
Kisspeptin research is scientifically interesting. It does not justify a consumer ranking of “best peptides for testosterone.” Keep the distinction between hormone response and proven treatment benefit clear, and discuss persistent symptoms with a qualified healthcare professional before pursuing a hormone intervention.
Frequently Asked Questions
Which peptide has human evidence for raising testosterone?
Kisspeptin has produced testosterone responses in some human research. The population, route, duration and endpoints limit what those findings establish. They are not a self-treatment recommendation.
Does ipamorelin reliably increase testosterone?
The evidence discussed here does not establish it as an effective testosterone treatment. Claims about growth hormone or recovery do not answer that clinical question.
Is BPC-157 a safe testosterone booster?
It should not be described that way. Human safety information is limited, and a proven testosterone-treatment benefit has not been established by the sources reviewed here.
Should I cycle peptides to avoid desensitization?
There is no universal cycling schedule that makes different peptides safe or effective. Do not apply a generic internet protocol; discuss the exact substance and indication with a qualified clinician.
Does a low result mean I need TRT?
One result alone does not determine treatment. Symptoms, repeat testing, underlying causes, fertility goals and individual risks all matter to the clinical decision.
Medical disclaimer: Educational editorial information only. This article has not received independent medical review and does not diagnose, prescribe or replace advice from your healthcare professional. Evidence checked September 12, 2026.







